Perioperative anaphylaxis
Anaesthetic reaction · Allergy / Immunology
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
Anaphylaxis under anaesthesia (commonly neuromuscular blockers, antibiotics, chlorhexidine or latex) often presents with sudden cardiovascular collapse and bronchospasm rather than a rash. Treat as anaphylaxis, stop the trigger and arrange later allergy testing with mast-cell tryptase samples.
Figures & algorithms
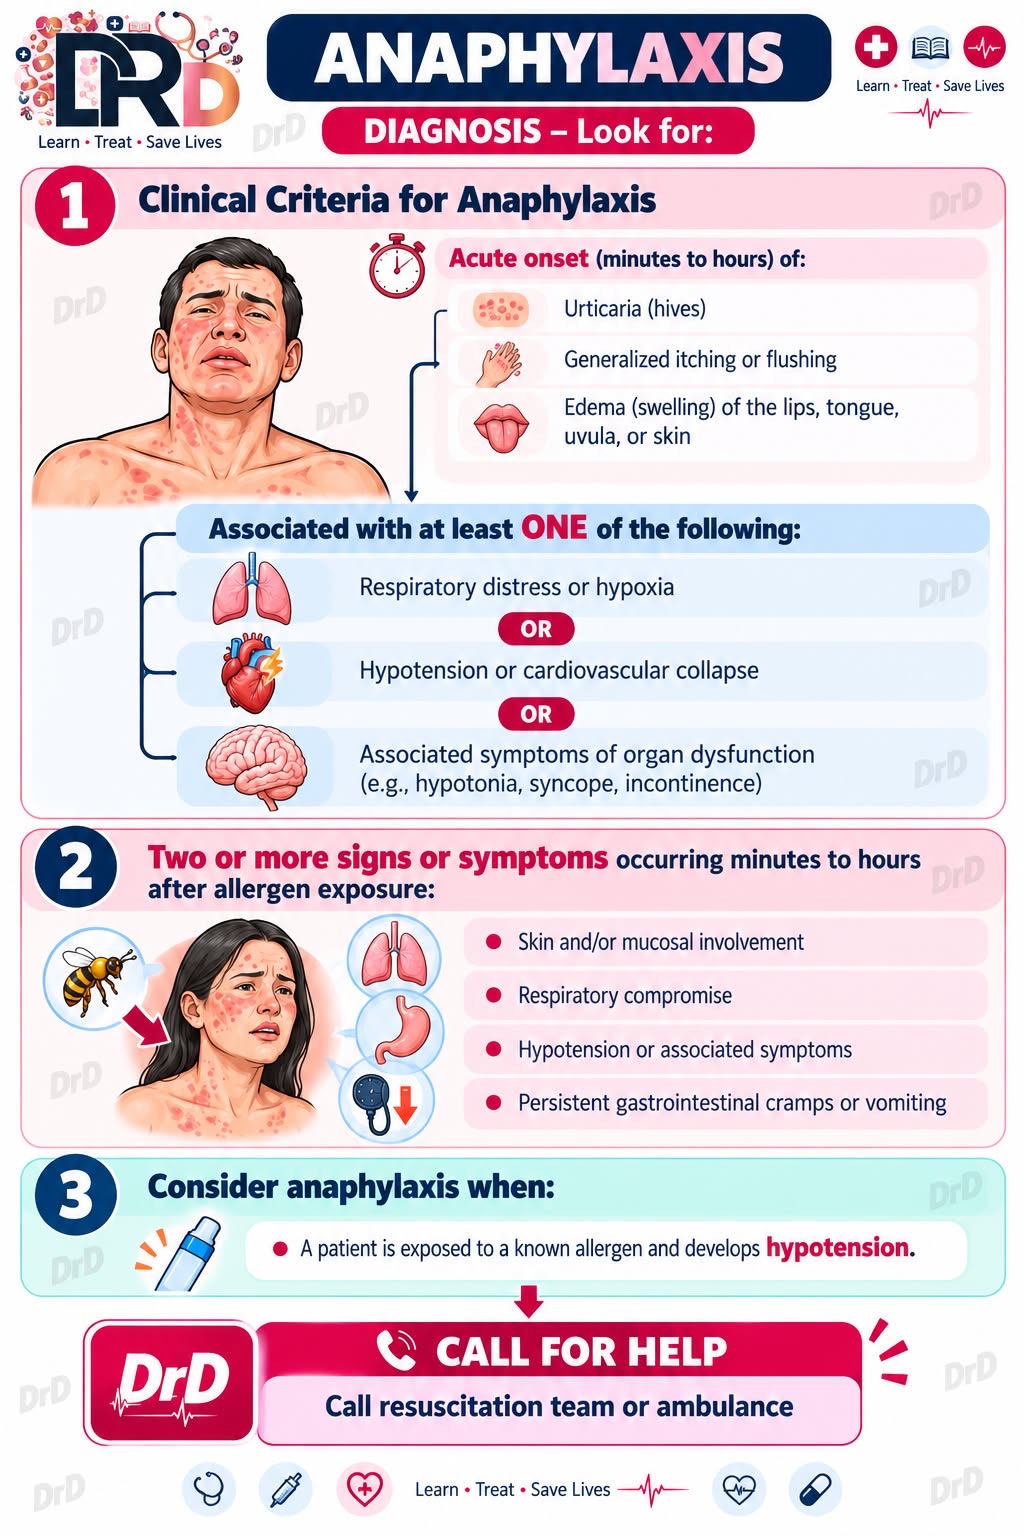
Assessment
Investigations
- Recognise collapse/bronchospasm/high airway pressures
- Serial mast-cell tryptase (immediate, 1-2 h, baseline)
- Document all agents given
Management
- Stop the likely trigger; call for help
- IM/IV adrenaline and aggressive IV fluids
- High-flow oxygen; treat bronchospasm
- Adrenaline infusion if refractory
- Take tryptase samples and refer for allergy investigation
Drugs & doses
Adrenaline (IM 500 mcg or IV titrated by anaesthetist)
IV fluids
Disposition
ICU; allergy referral.
Sudden collapse and high airway pressures under anaesthesia may be anaphylaxis without any rash - give adrenaline and send timed tryptase.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.