Adult epiglottitis (supraglottitis)
Airway · Respiratory
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
Life-threatening inflammation of the epiglottis and supraglottic structures in adults, presenting with rapid-onset severe sore throat, odynophagia, drooling, muffled voice and impending airway obstruction.
Figures & algorithms
Red flags
- Stridor, drooling, tripod positioning
- Rapidly worsening voice change / respiratory distress
- Cyanosis or exhaustion
- Inability to swallow secretions
Assessment
Differential diagnosis
- Peritonsillar/retropharyngeal abscess
- Ludwig angina
- Anaphylaxis / angioedema
- Foreign body
- Severe pharyngitis / croup
Investigations
- Do NOT delay airway assessment for imaging
- Careful fibreoptic nasendoscopy by an airway specialist (in a controlled setting)
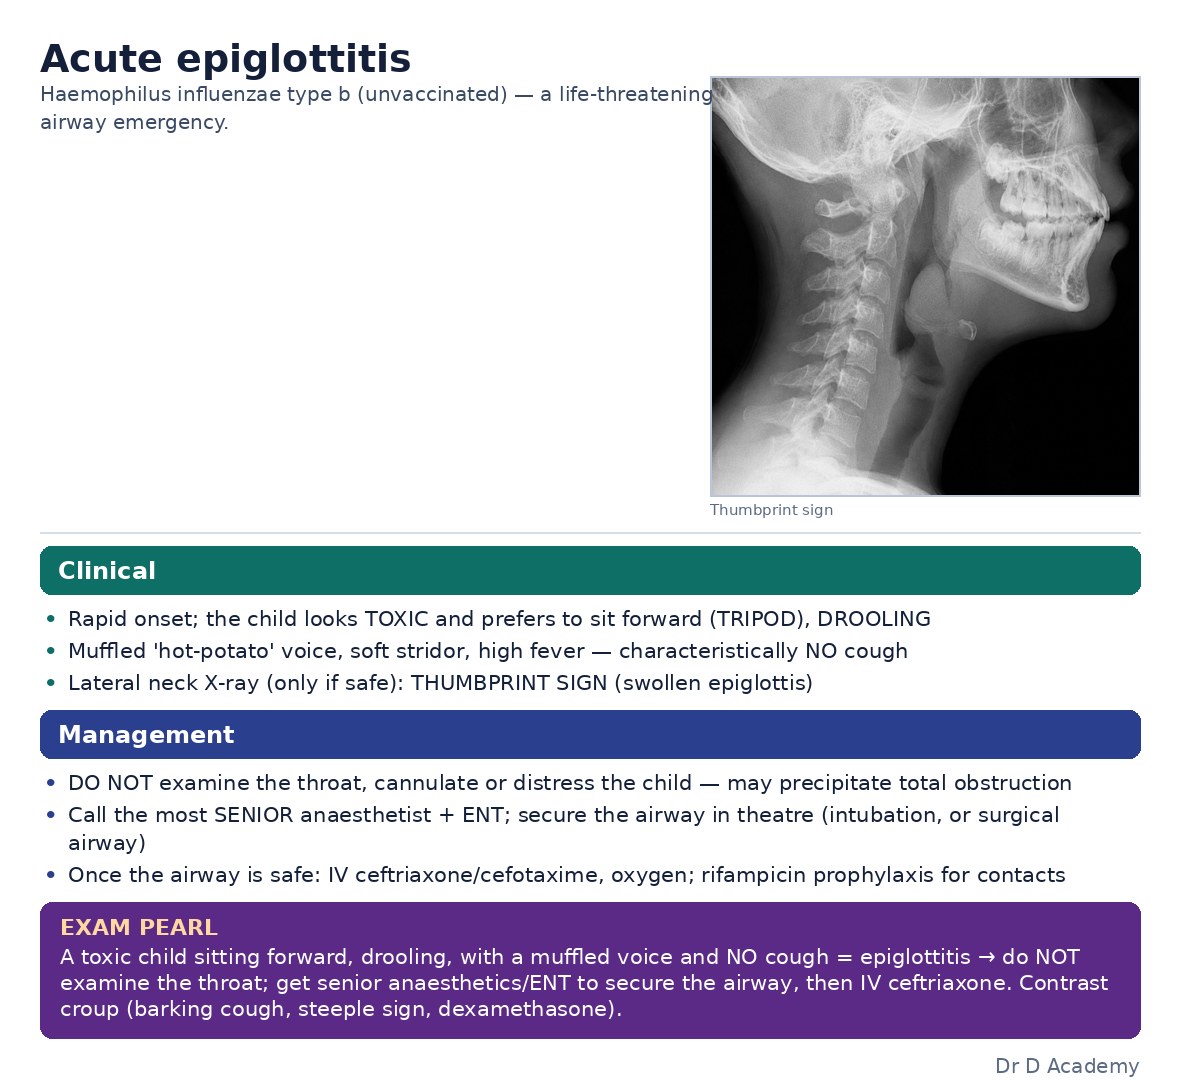
- Lateral neck X-ray (thumbprint sign) only if stable
- Blood cultures once airway secured
- FBC, CRP
Management
- Keep the patient calm and upright; do NOT examine the throat with a tongue depressor or lie the patient flat
- Give oxygen (humidified) and call for senior anaesthetic/ENT airway help immediately
- Prepare for a difficult airway with plans for fibreoptic intubation and surgical airway (double set-up)
- Give IV antibiotics after the airway is assessed/secured
- Consider nebulised adrenaline and steroids as temporising measures
- Admit for monitoring in a critical care/theatre environment
Drugs & doses
IV third-generation cephalosporin (e.g. ceftriaxone) covering H. influenzae
Corticosteroids (dexamethasone) - adjunct to reduce oedema
Nebulised adrenaline as a temporising measure
Oxygen (humidified)
Disposition
ICU/theatre with secured or closely observed airway; ENT and anaesthetics.
Complications & pitfalls
- Complete airway obstruction / respiratory arrest
- Airway abscess
- Sepsis
- Death
Exam pearls
- Never lie the patient flat or instrument the pharynx - this can precipitate complete obstruction
- Airway management takes priority over antibiotics and imaging
- Have a surgical airway plan ready before attempting intubation
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.