Thrombotic thrombocytopenic purpura
Microangiopathy · Haematology / Oncology
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
A life-threatening thrombotic microangiopathy caused by severe ADAMTS13 deficiency, producing platelet-VWF microthrombi, microangiopathic haemolysis and organ ischaemia. Treat on microangiopathic haemolytic anaemia (MAHA) + thrombocytopenia alone — do NOT wait for the classic pentad. Untreated mortality is ~90%.
Figures & algorithms
Red flags
- Fluctuating neurology — confusion, seizure, focal deficit, coma
- Chest pain / troponin rise (cardiac microthrombi) — a major cause of death
- Acute kidney injury
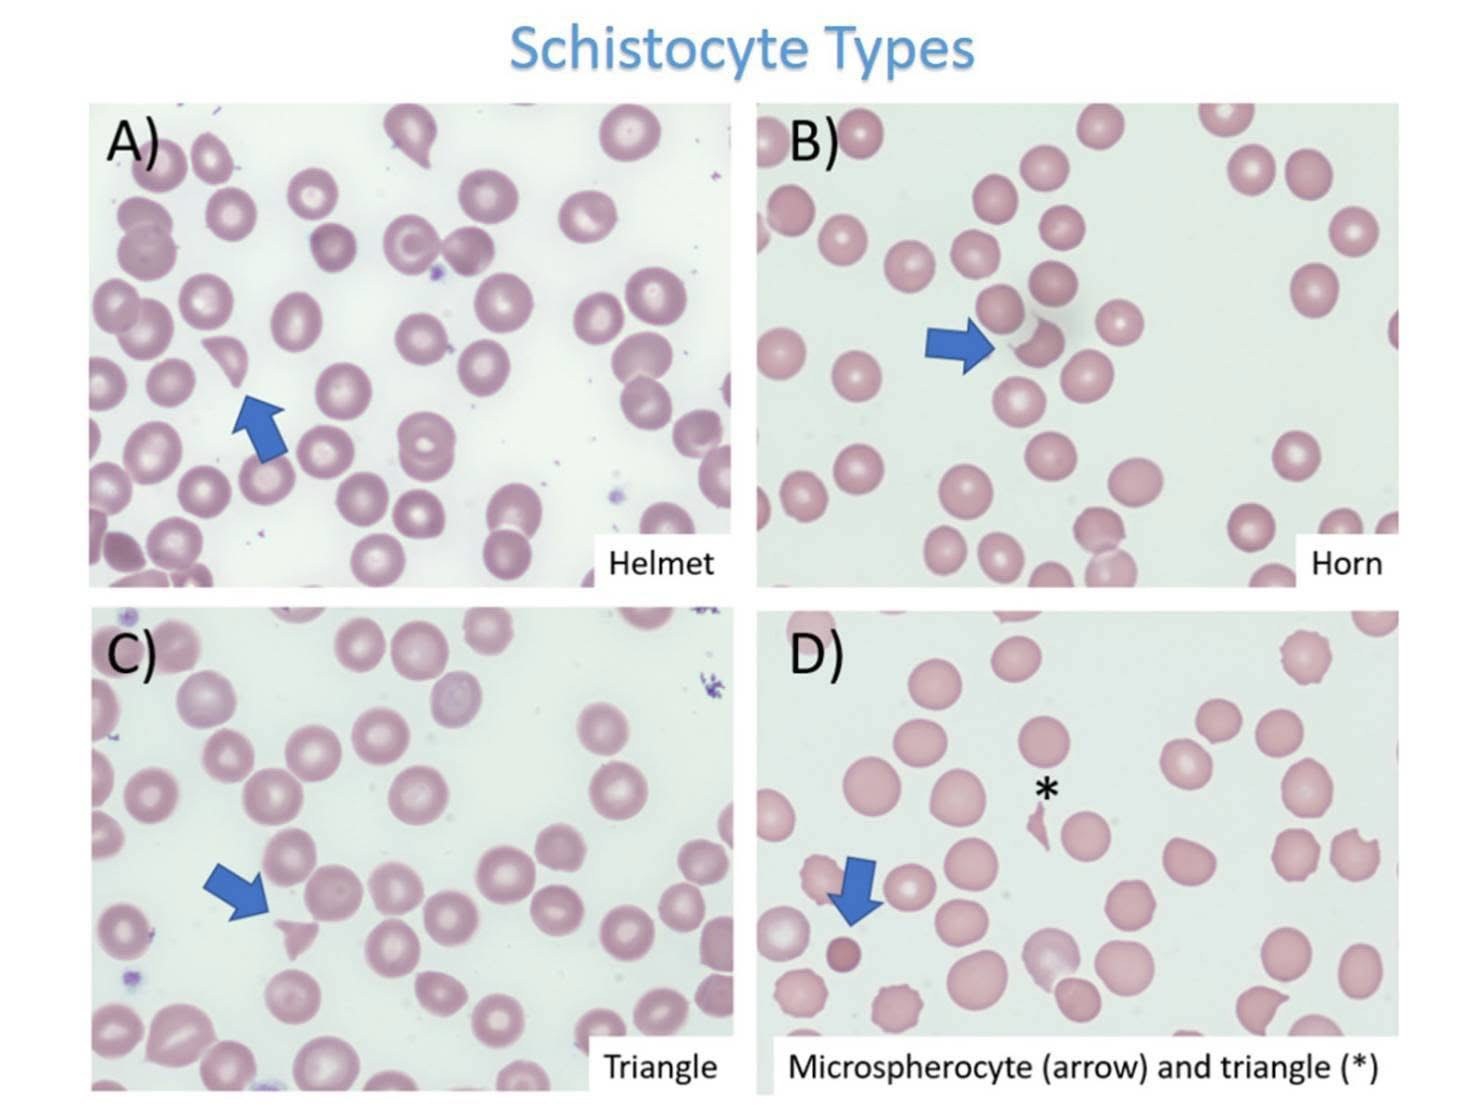
- Profound thrombocytopenia with schistocytes on film
Assessment
Differential diagnosis
- Haemolytic uraemic syndrome (HUS) — esp. E. coli O157 in children, renal-predominant
- DIC (abnormal coagulation, a source of sepsis/malignancy)
- HELLP / pregnancy-related TMA
- Malignant hypertension
- Severe sepsis
- Heparin-induced thrombocytopenia
- Evans syndrome
- Drug-induced TMA
Investigations
- FBC + blood film — SCHISTOCYTES + thrombocytopenia (the key finding)
- LDH markedly raised; bilirubin up; haptoglobin low; reticulocytes up
- Direct antiglobulin test (DAT/Coombs) NEGATIVE
- Coagulation screen NORMAL (distinguishes from DIC)
- U&E (renal), troponin (cardiac microthrombi)
- ADAMTS13 activity (<10%) + inhibitor — SEND BEFORE giving any plasma
- Pregnancy test
Management
- Recognise MAHA + thrombocytopenia with NORMAL coagulation = TTP until proven otherwise
- Immediate haematology + critical care referral — this is a haematological emergency
- Start urgent PLASMA EXCHANGE (PEX) — the definitive treatment; do not wait for the ADAMTS13 result
- High-dose corticosteroids (methylprednisolone / prednisolone)
- Caplacizumab (anti-VWF) early where available
- If PEX is delayed, give FFP infusion as a temporising bridge
- Folic acid; rituximab for immune TTP
- Do NOT transfuse platelets unless there is life-threatening bleeding
Drugs & doses
Plasma exchange (definitive)
Methylprednisolone / prednisolone
Caplacizumab
FFP (bridge only if PEX delayed)
Folic acid
Rituximab (immune TTP)
Disposition
Critical care / haematology for daily plasma exchange and monitoring.
Complications & pitfalls
- Death (untreated ~90%)
- Stroke, seizures
- Myocardial infarction / arrhythmia
- Acute kidney injury
- Relapsing / refractory disease
Exam pearls
- Normal PT/APTT with MAHA + thrombocytopenia points to TTP over DIC
- PLATELET TRANSFUSION IS CONTRAINDICATED except for life-threatening haemorrhage — it fuels the microthrombi
- Send ADAMTS13 (activity + inhibitor) BEFORE the first plasma/PEX
- Start plasma exchange the same day — outcome is time-critical
TTP is a true haematological emergency — start plasma exchange urgently. Platelet transfusion can be fatal (drives microthrombi) unless there is life-threatening bleeding.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.