Malignant bowel obstruction
Oncologic emergency · Haematology / Oncology
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
Mechanical or functional bowel obstruction from intra-abdominal/pelvic malignancy (commonly ovarian and colorectal), causing colicky pain, distension, vomiting and constipation.
Figures & algorithms
Red flags
- Peritonism, fever, rising lactate (perforation/ischaemia)
- Complete obstruction with faeculent vomiting
- Haemodynamic instability
Assessment
Differential diagnosis
- Adhesional obstruction
- Constipation/faecal impaction
- Ileus
- Volvulus
- Non-malignant stricture
Investigations
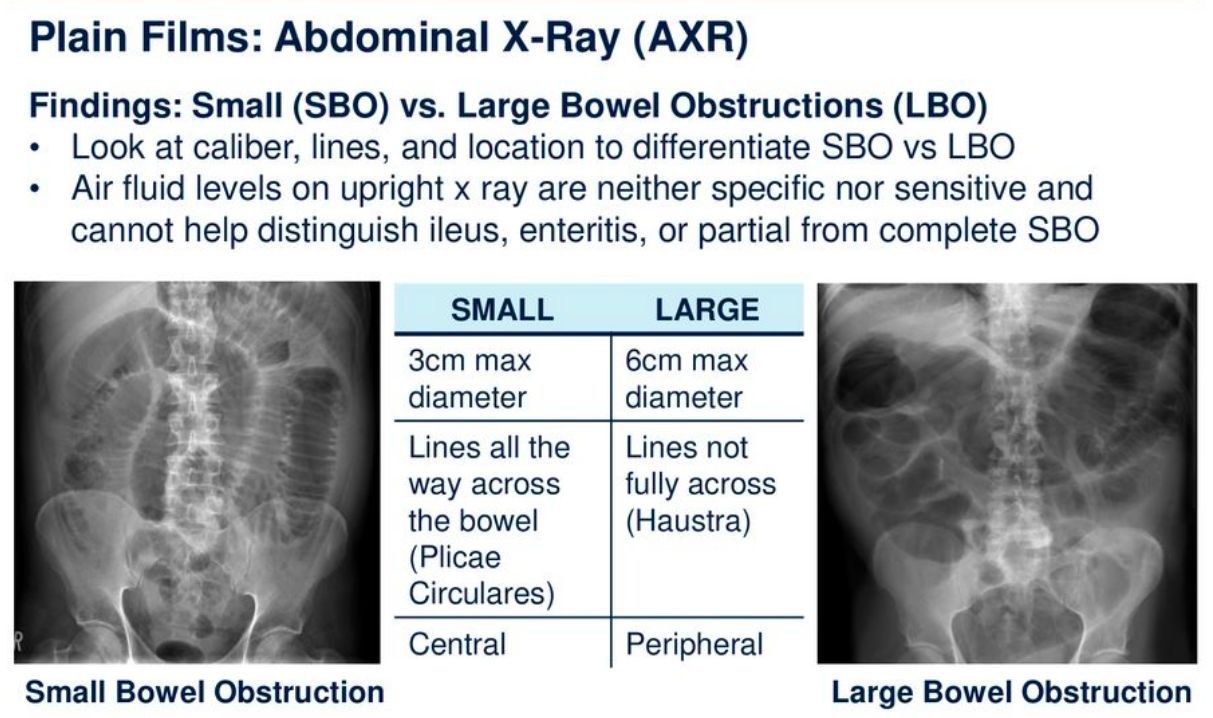
- Abdominal X-ray and CT abdomen/pelvis (level and cause)
- U&E, FBC, calcium, LFTs
- Venous gas, lactate (ischaemia)
- Group and save
Management
- Nil by mouth, IV fluids and electrolyte correction
- Nasogastric decompression for vomiting/distension ("drip and suck")
- Analgesia (opioid), antiemetics and antisecretory agents for symptom control
- Involve surgery and oncology - decide between surgery/stenting and medical/palliative management
- Consider corticosteroids and octreotide for symptom control if inoperable
Drugs & doses
IV fluids and electrolyte replacement
Antiemetics (e.g. metoclopramide if not complete obstruction/colic; otherwise cyclizine/haloperidol)
Opioid analgesia; hyoscine butylbromide for colic
Dexamethasone and octreotide for inoperable obstruction
Disposition
Admit under surgery; involve oncology and palliative care for management decisions.
Complications & pitfalls
- Bowel ischaemia/perforation
- Aspiration
- Electrolyte disturbance
- Recurrent obstruction
Exam pearls
- Avoid prokinetics (metoclopramide) in complete mechanical obstruction with colic.
- Management balances surgery/stenting against medical symptom control depending on prognosis and operability.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.