Testicular torsion
Urological emergency · Genitourinary
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
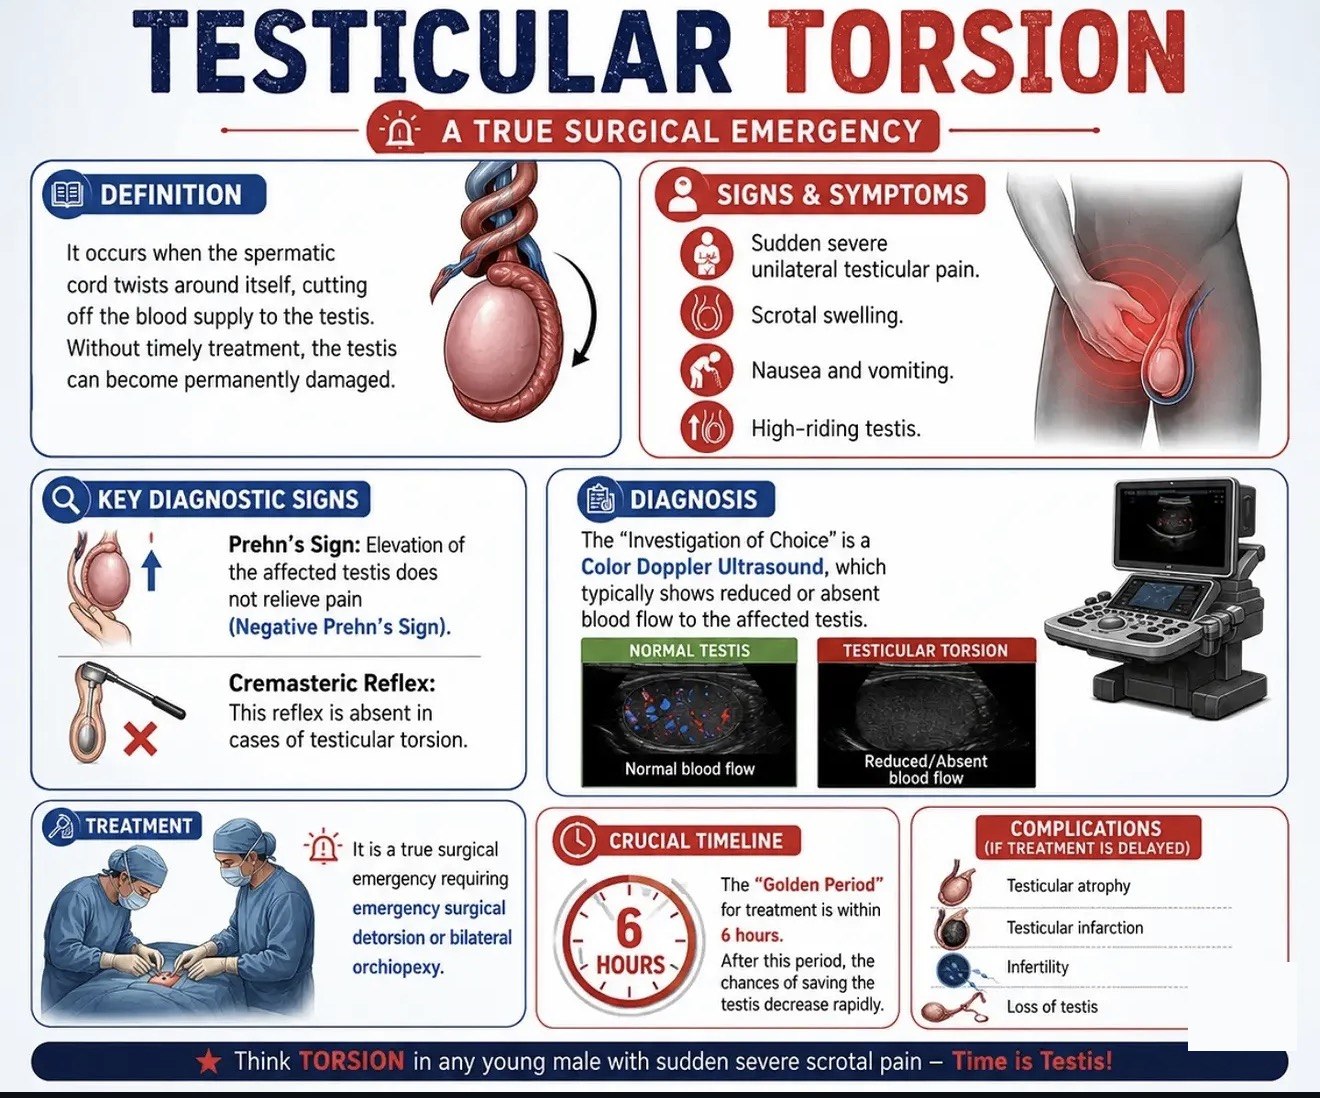
Twisted spermatic cord cutting off testicular blood supply. Sudden severe testicular pain; salvage falls sharply after ~6 hours. Clinical diagnosis — do not delay for imaging.
Figures & algorithms
Red flags
- Sudden severe pain, high-riding testis, absent cremasteric reflex
- Nausea/vomiting
- Short duration (salvageable)
Assessment
Differential diagnosis
- Epididymo-orchitis
- Torsion of a testicular appendage
- Strangulated hernia
- Trauma
- Renal colic (referred)
Investigations
- Clinical diagnosis (high-riding testis, absent cremasteric reflex)
- Do NOT delay surgery for ultrasound if clinically likely
- Pre-op bloods
Management
- Immediate urology referral for scrotal exploration
- Analgesia; nil by mouth; consent for orchidopexy ± orchidectomy
- Manual detorsion (“open book”) may temporise if surgery delayed
- Fix both testes at surgery
- Time is testicle — minimise delay
Drugs & doses
Analgesia, antiemetics
IV fluids; prepare for theatre
Disposition
Emergency urology/theatre.
Complications & pitfalls
- Testicular loss/infarction
- Subfertility
- Missed diagnosis
Exam pearls
- Clinical diagnosis — don’t wait for ultrasound
- Salvage rate falls rapidly after 6 hours
- Fix the contralateral testis too
Straight to theatre on clinical suspicion — imaging must not delay exploration.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.