New left bundle branch block with suspected MI
LBBB and ischaemia (Sgarbossa) · Cardiac
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
Chest pain with LBBB where acute coronary occlusion must be identified using Sgarbossa criteria rather than assuming LBBB masks all MI.
Figures & algorithms
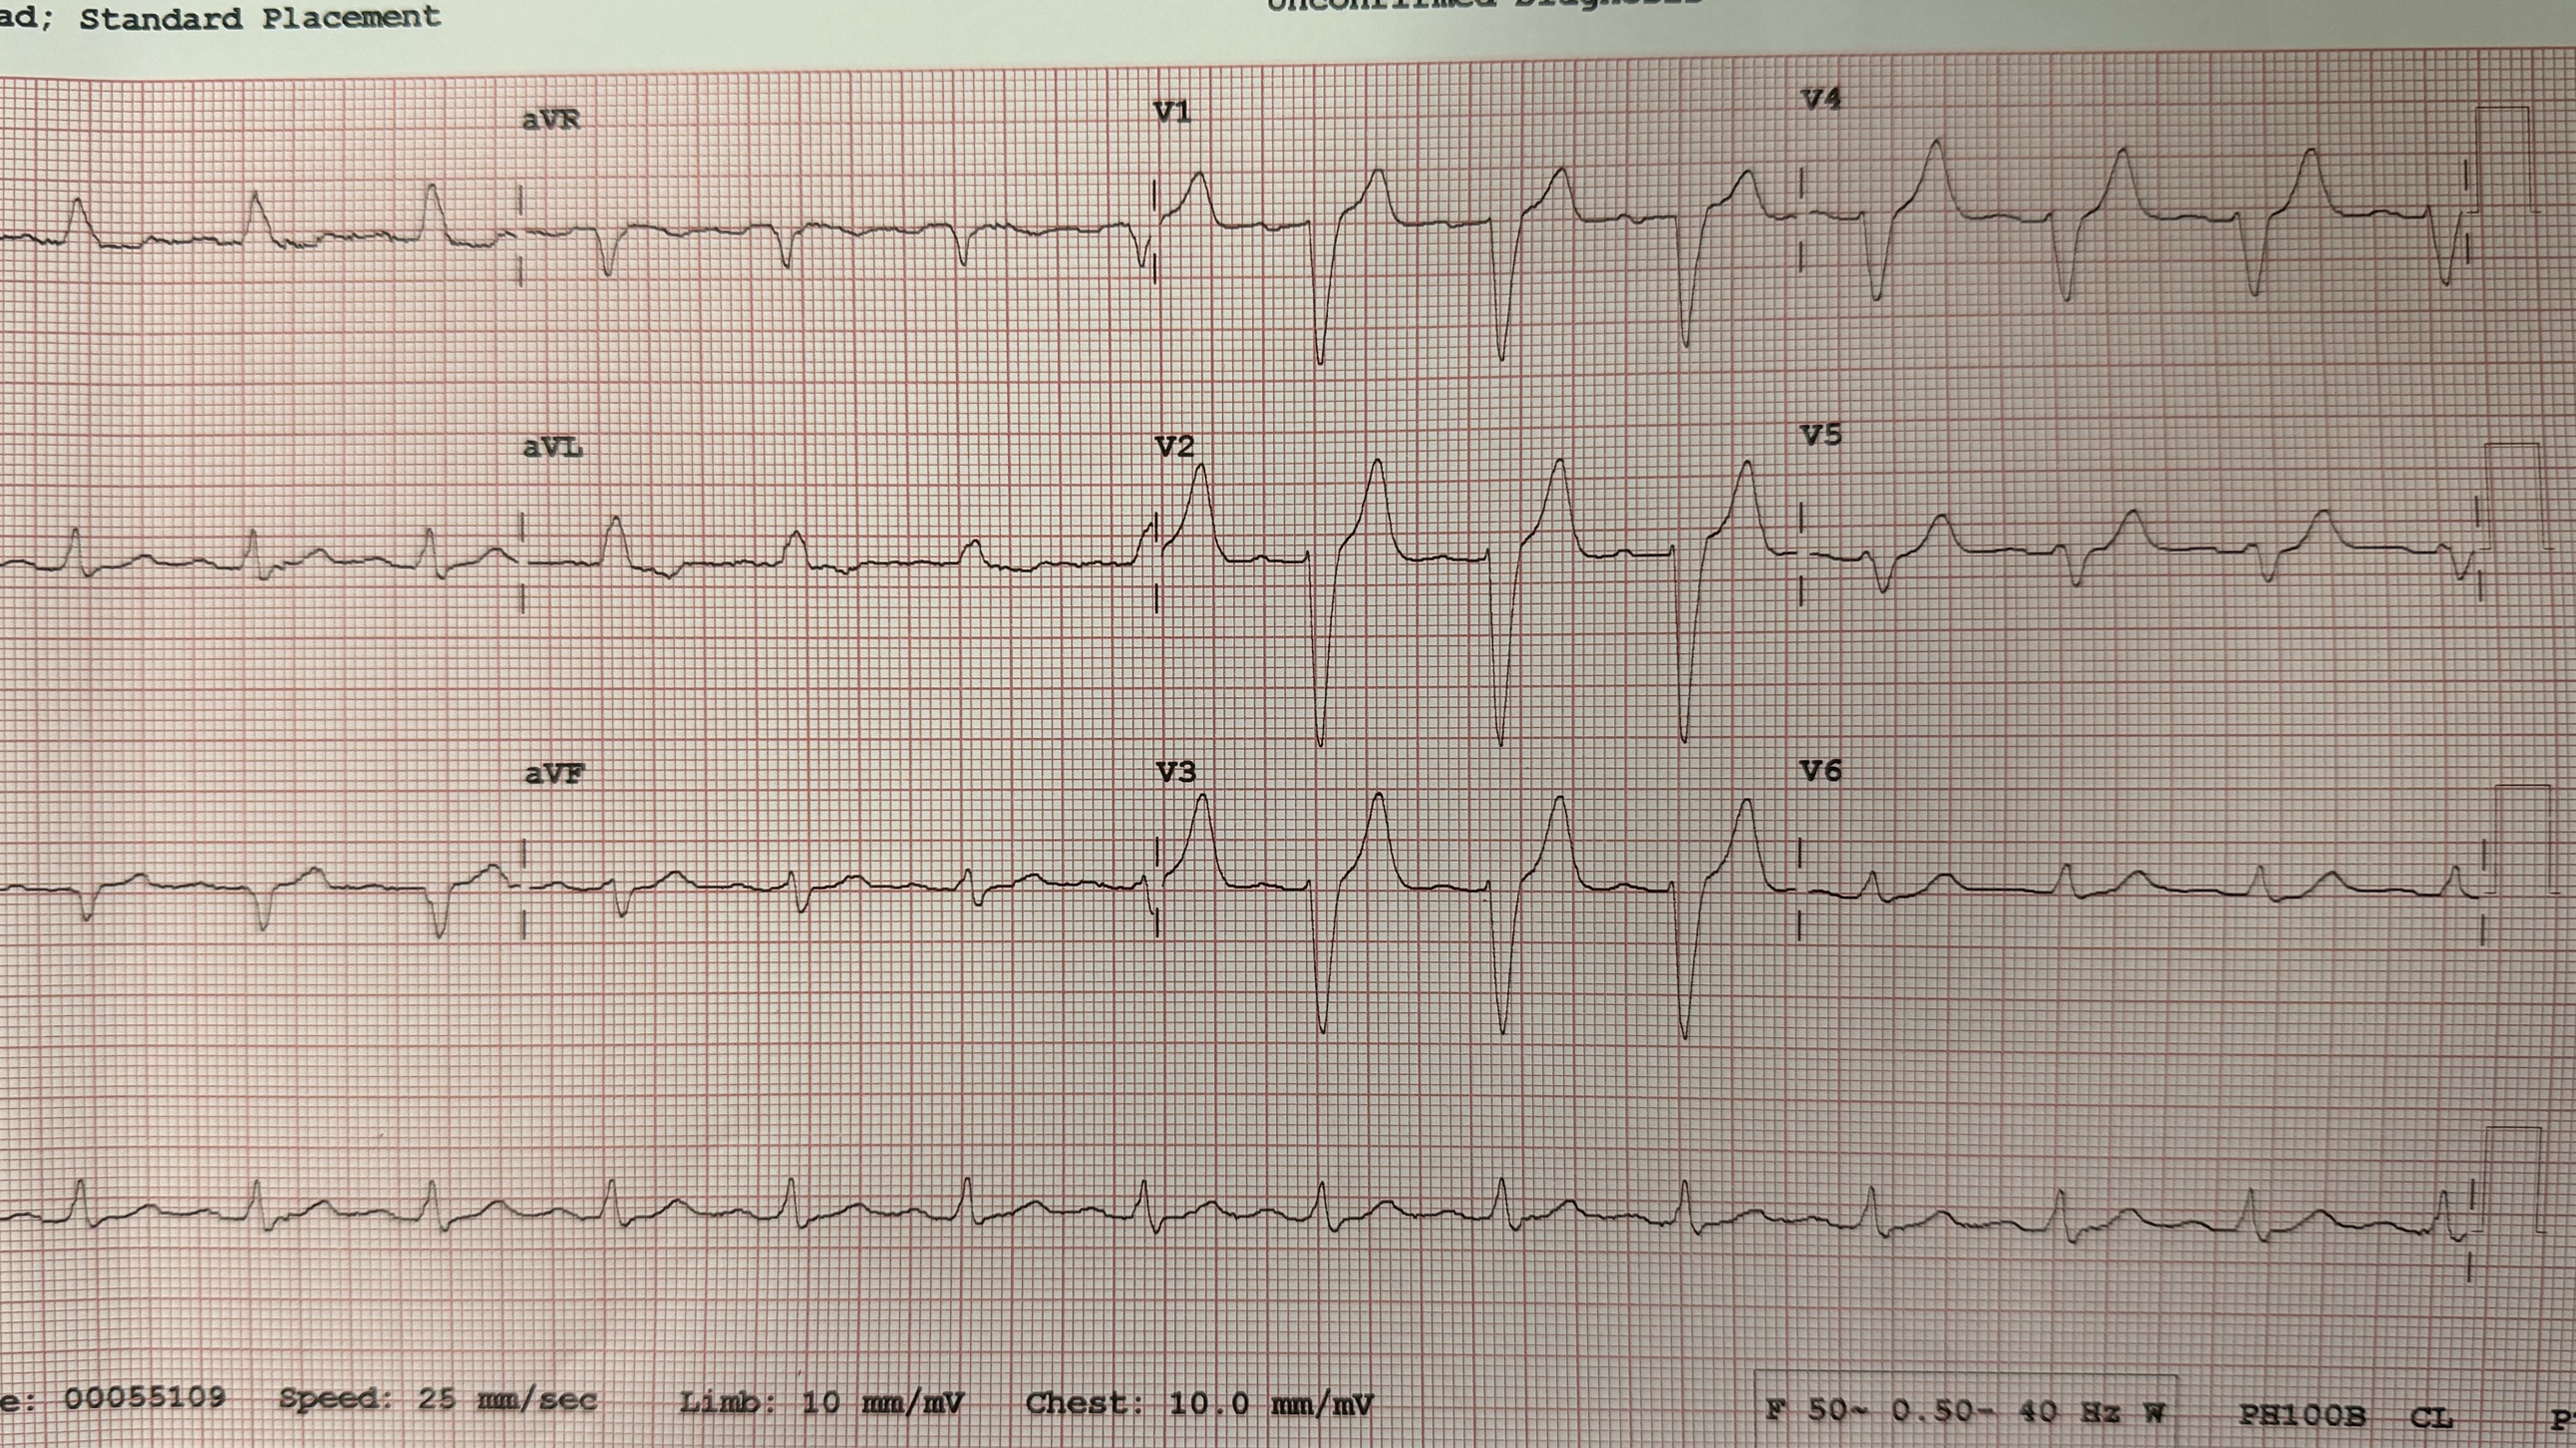
Red flags
- Concordant ST elevation >=1 mm
- Excessive discordant ST elevation
- Haemodynamic instability
- Ongoing pain
Assessment
Differential diagnosis
- Old/rate-related LBBB
- Paced rhythm
- LV hypertrophy strain
- Hyperkalaemia
- Pericarditis
Investigations
- Serial 12-lead ECGs (apply Sgarbossa/modified Sgarbossa)
- High-sensitivity troponin
- Compare with old ECG
- Bedside echo for wall motion
Management
- Assess for haemodynamic instability and ischaemic symptoms
- Apply modified Sgarbossa criteria to the ECG
- If criteria positive or unstable, activate primary PCI pathway
- Give aspirin and second antiplatelet plus anticoagulation per ACS pathway
- If criteria negative, treat as NSTEMI pathway with serial troponin
- Cardiology involvement early
Drugs & doses
Aspirin (antiplatelet) - 300 mg oral loading
Ticagrelor (P2Y12 inhibitor) - loading per local ACS pathway
Unfractionated/LMW heparin (anticoagulant) - per pathway
Disposition
Cath lab if criteria positive/unstable; otherwise CCU with serial troponin.
Complications & pitfalls
- Missed occlusion MI
- Arrhythmia
- Cardiogenic shock
Exam pearls
- New LBBB alone is not an automatic STEMI activation
- Modified Sgarbossa (Smith) improves sensitivity
- Always seek an old ECG
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.