Giant cell (temporal) arteritis
Vasculitis · Vascular
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
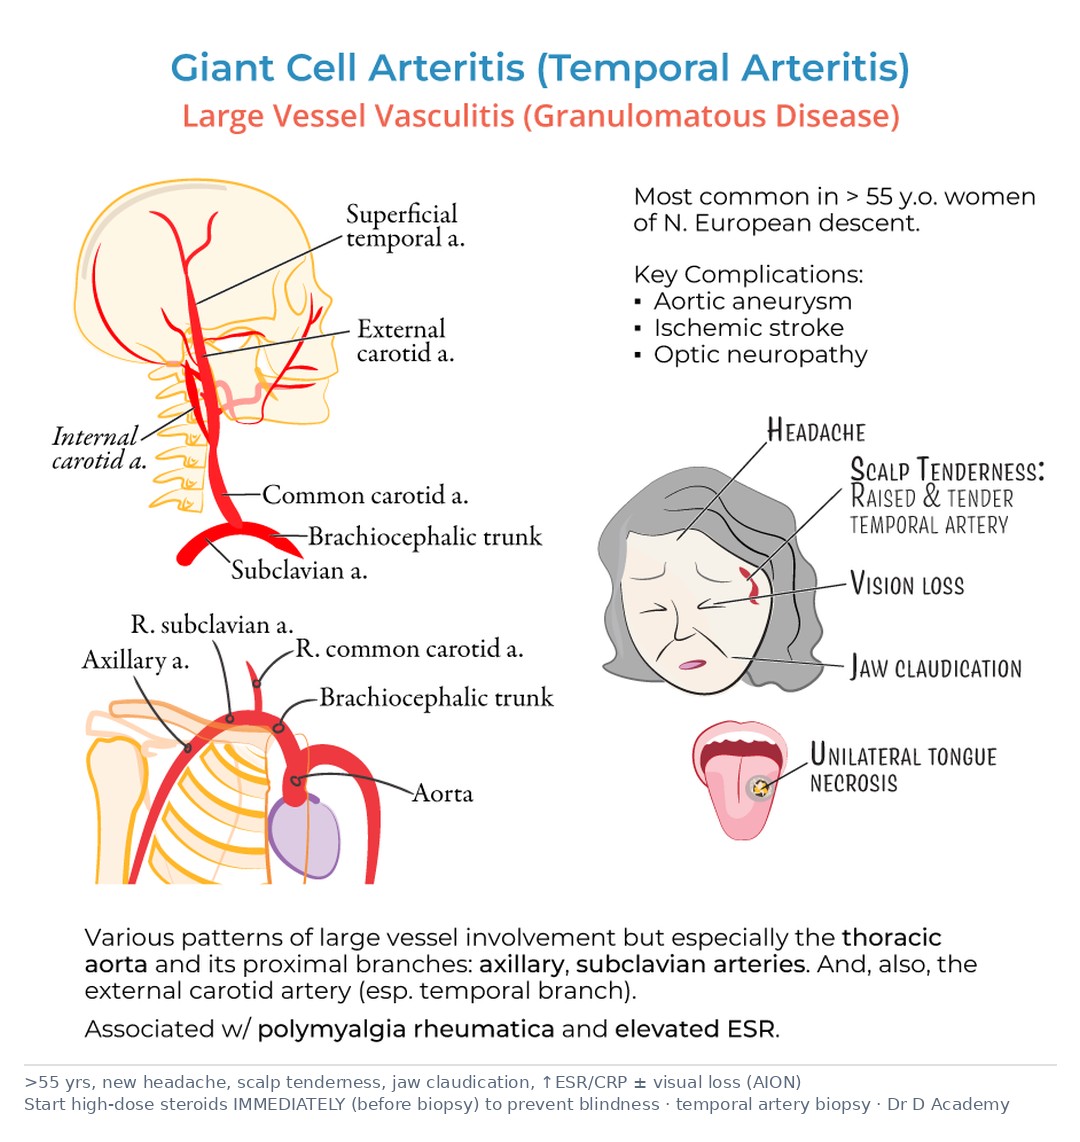
Granulomatous large-vessel vasculitis in patients >50, threatening irreversible blindness via anterior ischaemic optic neuropathy. A treat-first, confirm-later emergency.
Figures & algorithms
Red flags
- Any visual loss / amaurosis fugax (impending blindness)
- Jaw claudication
- Diplopia
- Stroke-like symptoms (large-vessel involvement)
Assessment
Differential diagnosis
- Tension/migraine headache
- Trigeminal neuralgia
- Acute angle-closure glaucoma
- Central retinal artery occlusion
- Other optic neuropathy
- Cervical spondylosis
Investigations
- ESR and CRP (usually markedly raised)
- FBC (normocytic anaemia, thrombocytosis)
- Temporal artery ultrasound (halo sign) / biopsy
- Ophthalmology assessment
Management
- Suspect in new headache + scalp tenderness + jaw claudication + visual symptoms (age >50)
- Start high-dose corticosteroid IMMEDIATELY — do not wait for biopsy
- IV methylprednisolone if visual symptoms; otherwise high-dose oral prednisolone
- Urgent ophthalmology + rheumatology referral
- Arrange temporal artery biopsy within ~1–2 weeks (steroids will not negate it quickly)
- Gastroprotection + bone protection with steroids
Drugs & doses
Prednisolone 40–60 mg PO daily (no visual loss)
IV methylprednisolone (visual involvement)
Aspirin; PPI; bone protection
Disposition
Admit visual cases for IV steroids; urgent ophthalmology + rheumatology; GCA fast-track clinic.
Complications & pitfalls
- Irreversible blindness
- Aortic aneurysm/dissection (large-vessel)
- Stroke
- Steroid side-effects
Exam pearls
- Visual loss is often irreversible — steroids protect the SECOND eye
- A normal ESR does not fully exclude it; use CRP and clinical picture
- Do not delay steroids for the biopsy
Sight-threatening — give high-dose steroids on clinical suspicion, before biopsy.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.